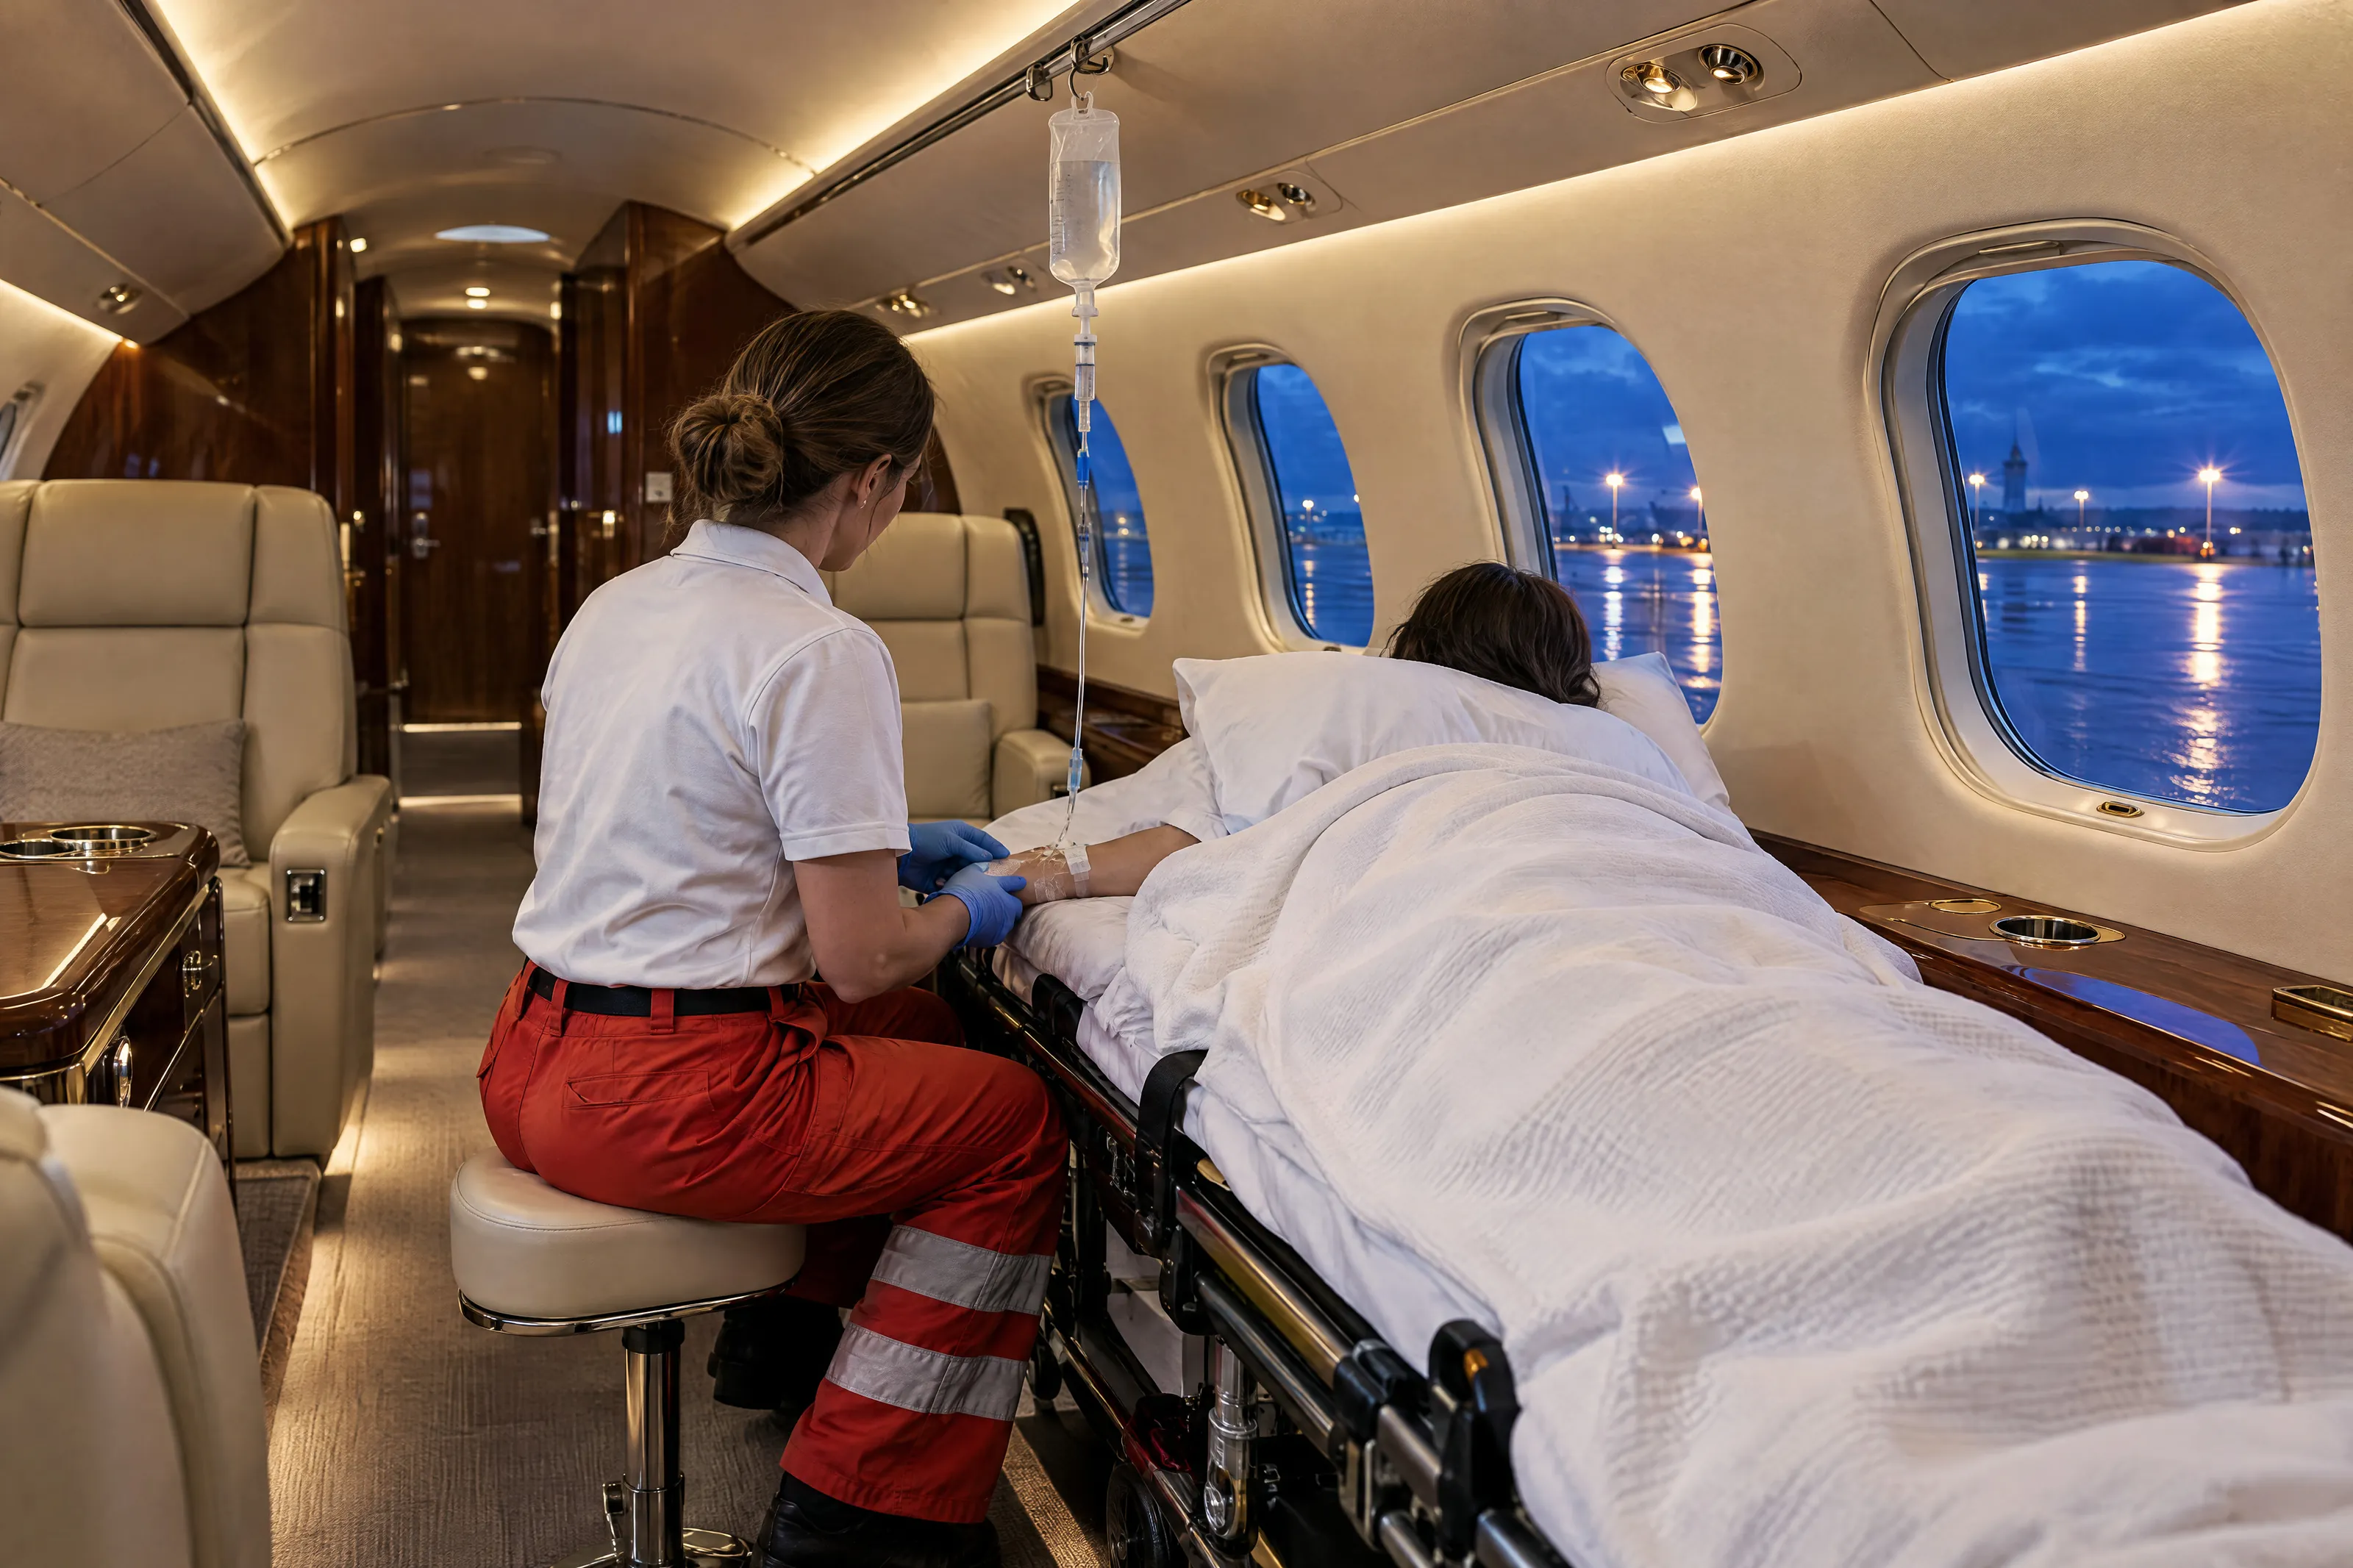
ICU at home
ICU at home: what it takes to run intensive care outside a hospital
What intensive care means, what a team and its equipment need to deliver it in a private home, who can be treated there safely, and the plan for the moment a hospital is needed.

In short
- Intensive care is defined by the support a patient needs, not by the building: the UK’s Intensive Care Society says its levels of care describe the care a patient requires, not where they receive it.1
- At the highest level, UK standards require at least one registered nurse for every patient, and a consultant who is available around the clock and can attend within 30 minutes.2
- Long-term ventilation at home depends on duplicated equipment and trained people: German guidance requires two approved ventilators when ventilation is life-sustaining for more than 16 hours a day, and US guidance for children asks for a trained caregiver awake in the home at all times.34
- The official models of acute care at home all require a defined route back to hospital; in Dubai, home healthcare teams should have an agreement with a hospital for emergency transfer.5
- Recovery continues long after discharge: recent meta-analyses put the share of intensive care survivors with post-intensive care syndrome at about 54 to 60 percent.67
Intensive care is usually imagined as a place: a unit with glass walls, alarms and a nurse at every bed. Clinically it is a level of support, and some of that support is already delivered at home every day, for example as long-term ventilation.8 What cannot be moved is the standard. The team, the equipment and the plan for the moment things change have to come with the patient.
This guide explains what the levels of intensive care mean, what a team and its equipment need, who can and who cannot be cared for safely at home, and what recovery after intensive care involves. It is general information, not medical advice: whether a particular patient can be treated at home is a decision for the treating physicians.
What intensive care means: the levels of care
In the UK, the Intensive Care Society sorts patients by the support they need. Its second edition, from 2021, defines four levels.1
| Level | What it covers |
|---|---|
| Ward care | Needs that normal ward care in an acute hospital can meet, including ward patients at risk of deterioration1 |
| Level 1: enhanced care | Closer observation or intervention than a ward can provide, including basic support for a single organ system1 |
| Level 2: critical care | Basic support for two or more organ systems, advanced support for one system other than breathing, or long-term advanced respiratory support1 |
| Level 3: critical care | Advanced respiratory support alone, or advanced support for two or more organ systems; mechanical ventilation is the first example given1 |
The society stresses that the levels describe the care a patient requires, not where they receive it.1 That is the starting point for any question about intensive care at home: the question is never whether a home can be an intensive care unit, but whether the care the patient needs can be delivered there to the same standard.
Germany has written this into law. Out-of-hospital intensive care is a statutory benefit for people who need the constant presence of a suitably qualified nurse, and it can be provided in the patient’s own household.9
The team: who has to be there
The Guidelines for the Provision of Intensive Care Services (GPICS), published in a third version in January 2026 by the UK’s Faculty of Intensive Care Medicine and the Intensive Care Society, set the minimum standards for hospital units.2
- At least one registered nurse for every level 3 patient, and one for every two level 2 patients, with professional judgement on each shift where needs are higher2
- A nurse in charge of each shift who has no patients of their own, around the clock2
- At least half of the nurses holding a post-registration qualification in critical care2
- A consultant in intensive care medicine leading daytime care seven days a week, with ward rounds twice a day2
- A responsible consultant available around the clock who, when not on site, can attend within 30 minutes2
These are hospital standards. We are not aware of an equivalent official standard for intensive care in a private home, so the hospital benchmark is the fair one to apply to anyone who offers it.
The equipment, and the backup for the equipment
The best-documented form of intensive care at home is long-term ventilation. About 5 percent of ventilated intensive care patients do not wean from the ventilator within 21 days, and some of them go home still ventilated.2 In Sweden, 33 in every 100,000 people used home mechanical ventilation in 2020 to 2022, and only 2 percent of new patients were ventilated invasively.8
Guidelines for ventilated children at home list what has to be in the house:4
- A ventilator and a back-up ventilator, with batteries4
- A self-inflating bag and mask4
- Portable suction and a heated humidifier4
- Emergency oxygen, a nebuliser and a pulse oximeter4
For adults the same logic applies. German guidance requires two approved ventilators when ventilation is life-sustaining for more than 16 hours a day,3 and the NHS England specification for complex home ventilation requires 24-hour emergency access to advice and cover for equipment failure.10 In Great Britain, households that rely on medical equipment with a power supply can join their energy supplier’s Priority Services Register, which gives priority support in an emergency and, where possible, notice of planned power cuts.11
Who can be treated at home, and who cannot
Every official model of hospital-level care at home shares one condition: the patient must not need what only a hospital can provide.
- NHS England’s Hospital at Home for people living with frailty excludes patients who need diagnostics or interventions that are only available in hospital.12
- In Dubai, home healthcare patients must be medically stable and able to receive care at home without immediate hospitalisation.5
- The US Acute Hospital Care at Home programme admits patients only from an emergency department or an inpatient bed, with at least two in-person visits a day.13
- For a ventilated child, discharge home requires medical stability, unchanged ventilator and oxygen settings for at least several days, and the home equipment tried in hospital for 24 to 48 hours.4
That separates two situations that are easy to confuse. A patient on stable long-term ventilation, which the Intensive Care Society classes as level 2 care, can live at home with the right team and equipment.110 A patient in an acute crisis who needs advanced support for several organs needs a hospital intensive care unit, which every official model of care at home excludes.125 Intensive care at home sits between the two: it holds a stable patient at intensive-care standard, and it gets a patient whose condition changes to the right unit without delay.
The plan for the moment things change
What makes care at home safe is less the equipment than the route back. Official guidance names the same elements again and again.
A named clinical lead
NHS England expects Hospital at Home to be led by a named consultant or a suitably trained GP, with specialist advice available in and out of hours.12
Advice around the clock
Families caring for a ventilated patient should have a 24-hour helpline for clinical and equipment questions.14
A plan the patient and family know
NICE expects patients cared for on a respiratory virtual ward to be supported with a self-escalation plan of their own.15
Hospital-at-home programmes measure exactly this. In the US, hospitals in the Acute Hospital Care at Home programme report every escalation back to the hospital and every unexpected death.13
After intensive care: recovery takes months
Leaving intensive care is not the end of the illness. Post-intensive care syndrome describes new or worsening problems in physical, cognitive or mental health that arise after critical illness and persist after the hospital stay, and the term also covers family members.16
How common it is depends on how it is measured. Two recent meta-analyses put the share of survivors affected at 54 percent and 60 percent, with very large differences between studies.76 In a cohort of 406 survivors of respiratory failure or shock, 64 percent had at least one problem after three months and 56 percent after twelve months.17
NICE guidance on rehabilitation after critical illness covers the whole stretch from the intensive care stay to two or three months after discharge,18 and for adults who spent more than four days in critical care and are at risk, it expects a review two to three months after discharge.19
Questions to ask anyone who offers intensive care at home
- Who leads the care, and are they available around the clock?212
- How many nurses per patient, and with what critical care experience?2
- Which equipment is duplicated, and what happens if the power fails?311
- Which hospital takes the patient if their condition changes, and how do they get there?514
- Who trains the family, and whom do they call at night?414
- Who plans the rehabilitation once the acute phase is over?18
Shadow ICU’s ICU at home starts from the same questions: clinicians and equipment are placed within reach and held for the full stay, dedicated to a single person, and the receiving hospital is agreed before it is needed.
Questions
Some intensive care can be delivered at home when the patient is stable and the team, the equipment and the escalation plan meet the standard of a hospital unit; long-term ventilation at home is the most common example. A patient who needs advanced support for several organs in an acute crisis needs a hospital intensive care unit.
For long-term ventilation, guidelines list a ventilator and a back-up ventilator with batteries, a self-inflating bag and mask, portable suction, a heated humidifier, emergency oxygen, a nebuliser and a pulse oximeter. German guidance requires two approved ventilators when ventilation is life-sustaining for more than 16 hours a day.
The UK Guidelines for the Provision of Intensive Care Services (Version 3, 2026) set a minimum of one registered nurse for every level 3 patient and one for every two level 2 patients, with a nurse in charge of each shift who has no patients of their own.
Post-intensive care syndrome describes new or worsening problems in physical, cognitive or mental health that arise after critical illness and persist after the hospital stay. Family members can be affected too. Recent meta-analyses put its prevalence among survivors at about 54 to 60 percent, with large differences between studies.
Official models of acute care at home require a defined escalation route: a named lead clinician, advice around the clock, an agreed receiving hospital and a way back into hospital. In Dubai, home healthcare teams should have an agreement with a hospital for emergency transfer.
No. NHS Hospital at Home and the US Acute Hospital Care at Home programme provide hospital-level care at home for patients who would otherwise be on a ward, and they exclude patients who need interventions only a hospital can provide. Intensive care at home is a higher level of support and needs intensive-care staffing and equipment.
Sources
Every figure in this article is taken from the source given here, as published on the date shown.
- 1Intensive Care Society: Levels of Adult Critical Care, Second Edition: Consensus Statement, March 2021
- 2Faculty of Intensive Care Medicine and Intensive Care Society: Guidelines for the Provision of Intensive Care Services (GPICS), Version 3, January 2026
- 3Deutsche Gesellschaft für Pneumologie (AWMF register 020-008): S3-Leitlinie Nichtinvasive Beatmung als Therapie der chronischen respiratorischen Insuffizienz, 17 July 2024
- 4American Thoracic Society: Official Clinical Practice Guideline: Pediatric Chronic Home Invasive Ventilation (Sterni et al., Am J Respir Crit Care Med 2016), 15 April 2016
- 5Dubai Health Authority: Standards for Home Healthcare Services (DHA/HRS/HPSD/ST-57), effective 19 February 2025
- 6Annals of Medicine: Prevalence and incidence of post-intensive care syndrome among ICU survivors: a systematic review and meta-analysis (Zare-Kaseb et al.), 28 January 2026
- 7PLOS ONE: Prevalence of post-intensive care syndrome among ICU survivors and its association with ICU length of stay (Ayenew et al.), 8 May 2025
- 8CHEST Pulmonary: Evolution of Home Mechanical Ventilation in Sweden Over 27 Years (Palm et al.), 21 September 2024
- 9German Federal Ministry of Justice: Social Code Book V, § 37c: Außerklinische Intensivpflege, retrieved 7 October 2026
- 10NHS England: NHS Standard Contract for Respiratory: Complex Home Ventilation (Adult), A14/S/a, 2013/14
- 11Ofgem: Join your supplier’s Priority Services Register, retrieved 7 October 2026
- 12NHS England: Guidance note: Frailty virtual ward (Hospital at Home for those living with frailty), 22 December 2021
- 13Centers for Medicare & Medicaid Services: Acute Hospital Care at Home: information collection notice CMS-10950 (Federal Register 2026-07583), April 2026
- 14British Thoracic Society and Intensive Care Society: Model of Care for Specialised Weaning Units (BTS Reports, Vol 14, Issue 1), 2023
- 15NICE: Acute respiratory infection in over 16s: initial assessment and management including virtual wards (QS210), 31 October 2023
- 16Critical Care Medicine: Improving long-term outcomes after discharge from intensive care unit: report from a stakeholders’ conference (Needham et al.), February 2012
- 17Critical Care Medicine: Co-Occurrence of Post-Intensive Care Syndrome Problems Among 406 Survivors of Critical Illness (Marra et al.), September 2018
- 18NICE: Rehabilitation after critical illness in adults (CG83), published 25 March 2009, last reviewed 29 June 2018
- 19NICE: Rehabilitation after critical illness in adults (QS158), 7 September 2017
General information, not medical advice. In an emergency, call the local emergency number.